
Menopause care, assessed and treated properly.
Too many women are told to endure symptoms that deserve a proper clinical conversation. Dr. Sana brings UK and US credentials, reproductive-medicine experience and an individual plan to every consultation.
MBBS · MRCOG (UK) · FACOG · FRM · MSc Sexual & Reproductive Medicine (UK)
Perimenopause is treatable
Symptoms usually begin years before periods stop, and they respond to treatment. Waiting until periods end is not necessary.
Early menopause needs a plan
When ovarian function declines before 45, bone, heart and fertility all need active consideration rather than reassurance alone.
The years after matter
Bone density and cardiovascular risk change after the last period. Those are the years where planned care makes the largest difference.
Care for the part of menopause you are in.
Perimenopause Care
Naming what is happening, and treating it
Menopause Hormone Therapy
Body-identical HRT, prescribed properly
Premature Ovarian Insufficiency
Menopause before 40, and what comes next
Surgical & Medical Menopause
After hysterectomy, ovary removal or cancer treatment
Genitourinary Syndrome of Menopause
Dryness, painful sex and recurrent UTI — treatable
Bone & Heart Health
DEXA, lipids and the risk window after 45
Mood, Sleep & Brain Fog
The symptoms most often misdiagnosed
Non-Hormonal Care
When HRT is not an option
Menopause & 360° Wellness
Nutrition, movement and mind-body support
A hormonal change, not a character flaw.
Menopause is the point at which periods stop permanently because the ovaries produce progressively less oestrogen. In India it is commonly reported to occur somewhat earlier than in Western populations, and the years leading up to it — perimenopause — are when most symptoms actually begin.
It is a natural life stage rather than a disease. That does not mean it should be endured. Hormonal change affects sleep, mood, memory, bones, the heart, the bladder and sexual health, and effective treatment exists for almost all of it.
Many women in India are told their symptoms are stress, thyroid or simply age. A proper assessment separates those possibilities instead of guessing between them.

The symptoms that bring women here.
Oestrogen, progesterone and testosterone act throughout the body, so the symptom list is long and often does not look hormonal at first. These are the ones seen most often; the list is not exhaustive.
Cycle changes
- Shorter or longer cycles
- Heavier or lighter bleeding
- Spotting between periods
- Skipped periods
Emotional and cognitive
- Anxiety
- Low mood
- Irritability
- Brain fog
- Poor concentration
- Memory lapses
- Loss of confidence
Sleep and energy
- Difficulty falling asleep
- Waking at 3am
- Unrefreshing sleep
- Persistent fatigue
Vasomotor
- Hot flushes
- Night sweats
- Sudden sweating episodes
Musculoskeletal and pain
- Joint aches
- Muscle stiffness
- New or worsening migraine
- Frozen shoulder
Genitourinary and sexual health
- Vaginal dryness
- Pain with intercourse
- Urinary urgency
- Recurrent urine infections
- Reduced libido
Cardiac and physical
- Palpitations
- Weight and body-shape changes
- Dry or itchy skin
- Hair thinning
Not every menopause arrives the same way.
Natural menopause
Periods stop on their own. It is confirmed after twelve months without a period when no other cause explains it, though symptoms usually begin years earlier during perimenopause.
Early menopause and POI
Ovarian function declines before 45, or before 40 in premature ovarian insufficiency. This needs confirmation, a search for a cause, and a long-term plan for bone, heart and, where relevant, fertility.
Surgical menopause
Removal of both ovaries, often during hysterectomy for fibroids or endometriosis, causes an abrupt change rather than a gradual one. Symptoms are frequently more intense and begin within days.
Medical menopause
Chemotherapy, pelvic radiotherapy or hormone-suppressing treatment can stop ovarian function temporarily or permanently. Care has to account for the underlying condition.
Your consultation, step by step.
- 01
Share your history
Have your symptom history, current medicines and relevant reports ready before your appointment so the consultation can focus on decisions.
- 02
Assessment
A structured consultation covering symptoms, periods, medicines, family history and risk. Where investigations are useful, Dr. Sana specifies exactly which tests and why, at a lab near you.
- 03
A written plan
You receive a documented plan: what the diagnosis appears to be, the treatment options with their benefits and risks, and what to do if something changes.
- 04
Review and continuity
Menopause is rarely settled in one appointment. Reviews check whether treatment is working, and adjust it. Your local physician can be kept in the loop where you wish.

What treatment can involve.
Treatment is decided individually after assessment. Nothing below is a prescription, and doses are never set without a consultation.
Menopausal hormone therapy
Oestrogen, with progesterone where the uterus is present, in tablet, patch or gel form. Suitability, route and duration are individual decisions based on your symptoms, age, time since menopause and medical history.
Vaginal (local) oestrogen
For dryness, painful sex and recurrent urinary symptoms. It acts locally and is considered separately from systemic hormone therapy, including for many women who cannot take systemic HRT.
Non-hormonal prescription options
For women who cannot or prefer not to take hormones, several non-hormonal medicines have evidence for hot flushes, sleep and mood. These are chosen case by case.
Bone and heart protection
Vitamin D and calcium status, blood pressure, lipids, weight-bearing and resistance exercise, and bone-density assessment where indicated — especially after early or surgical menopause.
Symptom-directed support
Sleep strategies, treatment of migraine, pelvic-floor physiotherapy referral, and psychological support where mood symptoms are prominent.
Nutrition and movement in an Indian context
Practical protein, calcium, iron and vitamin D guidance built around Indian vegetarian and non-vegetarian diets, rather than generic Western meal plans.
What is different about this care.
Trained where menopause is a specialty
MRCOG (UK), FACOG and an MSc in Sexual and Reproductive Medicine from the University of South Wales. Menopause medicine is a formal part of that training; in most Indian OBG pathways it is not.
Guideline-based, not trend-based
Assessment and treatment follow published international menopause guidance rather than wellness marketing, supplements sold on commission, or unproven hormone testing.
Complex cases are welcome
Menopause after cancer treatment, surgical menopause, premature ovarian insufficiency and women previously told they cannot have hormone therapy are all within scope for a proper review.
Reproductive medicine background
Fertility and menopause are the same axis at different points. That matters for women with low ovarian reserve, POI, or those weighing family plans alongside symptoms.
Personal consultation
Every consultation is conducted by Dr. Sana herself and can be booked online at a time that suits you.
Care across borders
Video review appointments are available from anywhere in India and internationally, subject to local rules, with in-person assessment when clinically needed.
What women are told, and what is accurate.
“HRT causes breast cancer, full stop.”
The real picture depends on the type of therapy, your age, how long you use it and your own risk profile. It deserves a personalised conversation with actual numbers, not a blanket refusal.
“You are too young for this.”
Perimenopause often begins in the early forties, and ovarian insufficiency can occur before 40. Age alone is not a reason to dismiss symptoms.
“A blood test will tell you.”
In women over 45, menopause is a clinical diagnosis. Hormone levels fluctuate and a single normal result does not exclude perimenopause. Tests are more useful in younger women and in specific situations.
“Just bear it, it will pass.”
Symptoms can last several years, and some — bone loss, genitourinary changes — do not resolve on their own. Untreated symptoms have consequences for health, work and relationships.

What to have ready.
Bringing these to the consultation makes the assessment faster and more accurate. If you do not have all of it, the appointment still goes ahead.
- —Dates of your last few periods, or when they stopped
- —Your main three symptoms and how they affect daily life
- —A list of current medicines and supplements
- —Any past surgery, especially on the uterus or ovaries
- —Family history of breast cancer, clots, osteoporosis or early menopause
- —Recent blood pressure reading and any recent blood reports
The part nobody schedules around.
Perimenopause usually arrives in the busiest decade of a woman's life: senior responsibility at work, teenage children, ageing parents. Broken sleep, brain fog and unpredictable bleeding are not a private inconvenience — they change how the day goes.
Consultations account for that. Treatment decisions consider shift work, travel, exam seasons at home, and whether a daily tablet or a weekly patch is realistically easier for you to keep up.
Book an online consultation →
Continue reading on menopause
Check your symptom pattern
A validated symptom score, not a diagnosis. Rate how much each symptom troubles you now. Your answers remain only on this screen and are never stored or transmitted.
Heart beating quickly or strongly
Source: Greene JG. Constructing a standard climacteric scale. Maturitas. 1998;29(1):25–31.
Menopause is a stage, not a single day.
Perimenopause
Hormones and cycles begin to fluctuate. Symptoms may start while periods are still regular.
Menopause
The point confirmed after 12 months without a period, when no other cause explains it.
Early postmenopause
Symptoms may continue while bone, heart and genitourinary health deserve active attention.
Late postmenopause
Care shifts towards healthy ageing, prevention and treatment of persistent symptoms.
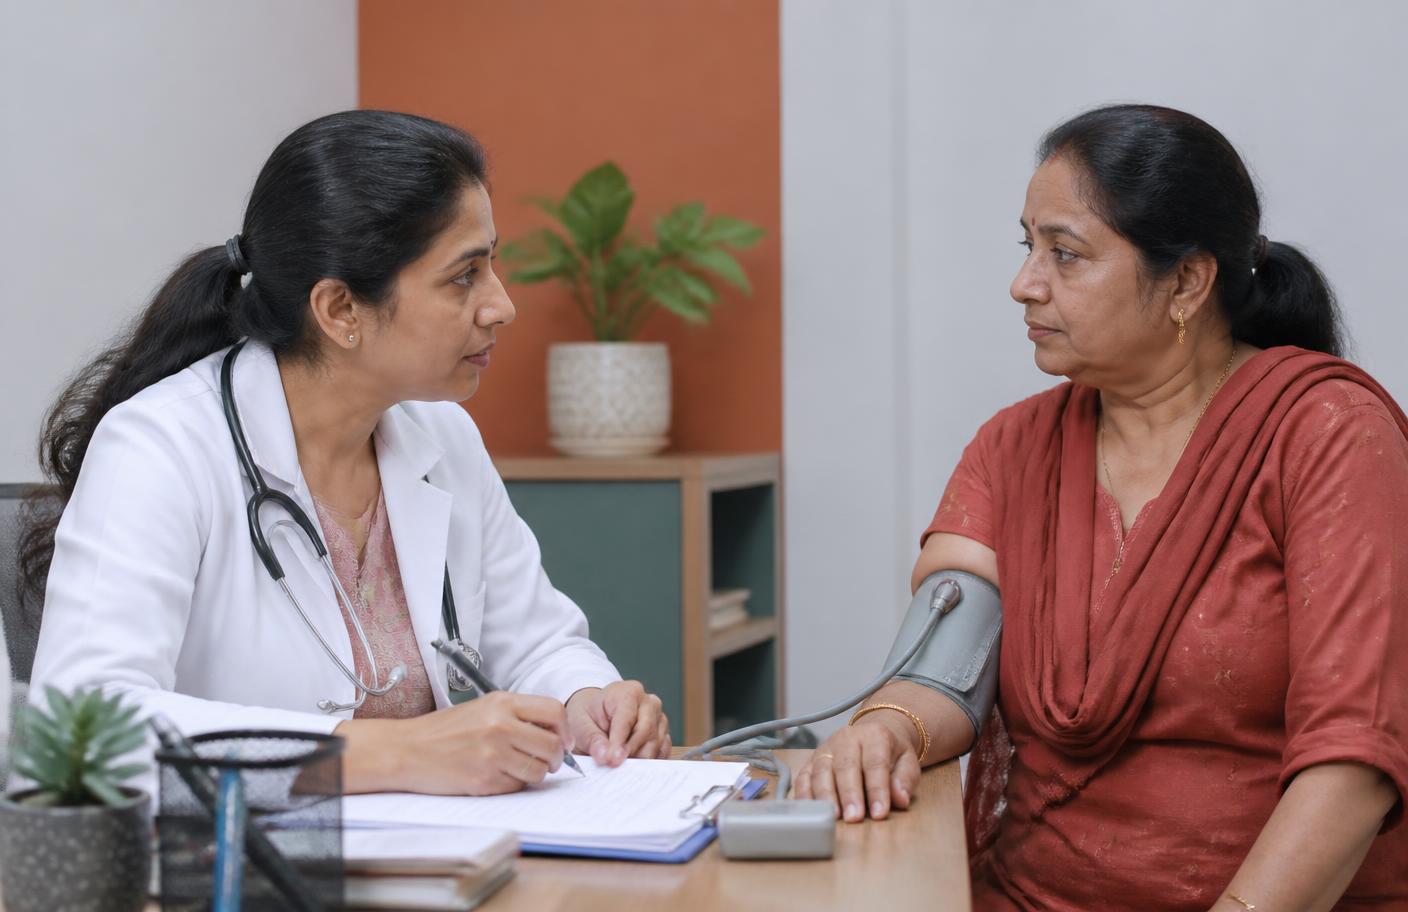
A careful history can begin from your own home.
Most menopause consultations begin with listening: your symptoms, menstrual history, medicines, risks and priorities. A blood-pressure reading and selected investigations may follow. When an examination, scan or procedure is needed, Dr. Sana explains why and arranges appropriate in-person care, including at Apollo in Hyderabad where relevant.
- Consult Dr. Sana personally
- Receive a documented, individual care plan
- Escalate to in-person care when clinically necessary
Fertility and menopause belong in the same conversation.
Dr. Sana's MSc in Sexual & Reproductive Medicine from the University of South Wales, MRCOG and FACOG inform the way she approaches this stage of life. In 2025, she published a case report on successful pregnancy and live birth after hormone replacement in a patient with premature ovarian insufficiency — a condition where fertility, hormone health and long-term wellbeing meet.
Answers before your consultation
What is the difference between perimenopause and menopause?+
Perimenopause is the transition during which ovarian hormone patterns and periods begin to change. Menopause is confirmed after twelve consecutive months without a period, provided there is no other medical explanation. Symptoms can begin years before that point and may continue afterwards.
At what age does menopause usually start in India?+
Population studies suggest the average is earlier in India than in many Western populations, but an individual woman's timing varies. Menopause before 40 needs a specific assessment for premature ovarian insufficiency; symptoms or cycle changes at any age should not be dismissed without context.
Do I need a blood test to know if I am in perimenopause?+
Often, no. In women over 45, symptoms and menstrual history are usually more useful than a single fluctuating hormone result. Tests may be appropriate when symptoms begin unusually early, periods stop unexpectedly, pregnancy is possible, or thyroid and other conditions need to be excluded.
Can you treat menopause entirely online?+
Many consultations, symptom reviews and follow-ups can be completed online. I may ask for a blood pressure reading and relevant investigations. Examination, imaging or procedures require an appropriate in-person setting, and I will explain clearly when that is necessary.
What can you prescribe in an online consultation?+
Prescribing depends on a documented consultation, medical history, individual risks and applicable telemedicine guidance. I will not recommend hormone therapy from a message alone. Where remote prescribing is clinically appropriate, monitoring and follow-up are agreed at the same time.
When would an in-person visit to Apollo be needed?+
An in-person review may be needed for concerning bleeding, examination, imaging, procedures or findings that cannot be assessed safely by video. Dr. Sana practises at Apollo Fertility, Kondapur, Hyderabad. Video consultations are available to patients in India and internationally, subject to local rules.
From Instagram
Short notes on fertility, menopause and women's health, posted between clinics.
You do not have to work it out alone.
Discuss your symptoms and treatment options in a personal consultation with Dr. Sana.
Book a video consultation →Booking from abroad and having trouble paying online? Contact us for alternative payment options.
WhatsApp about payment