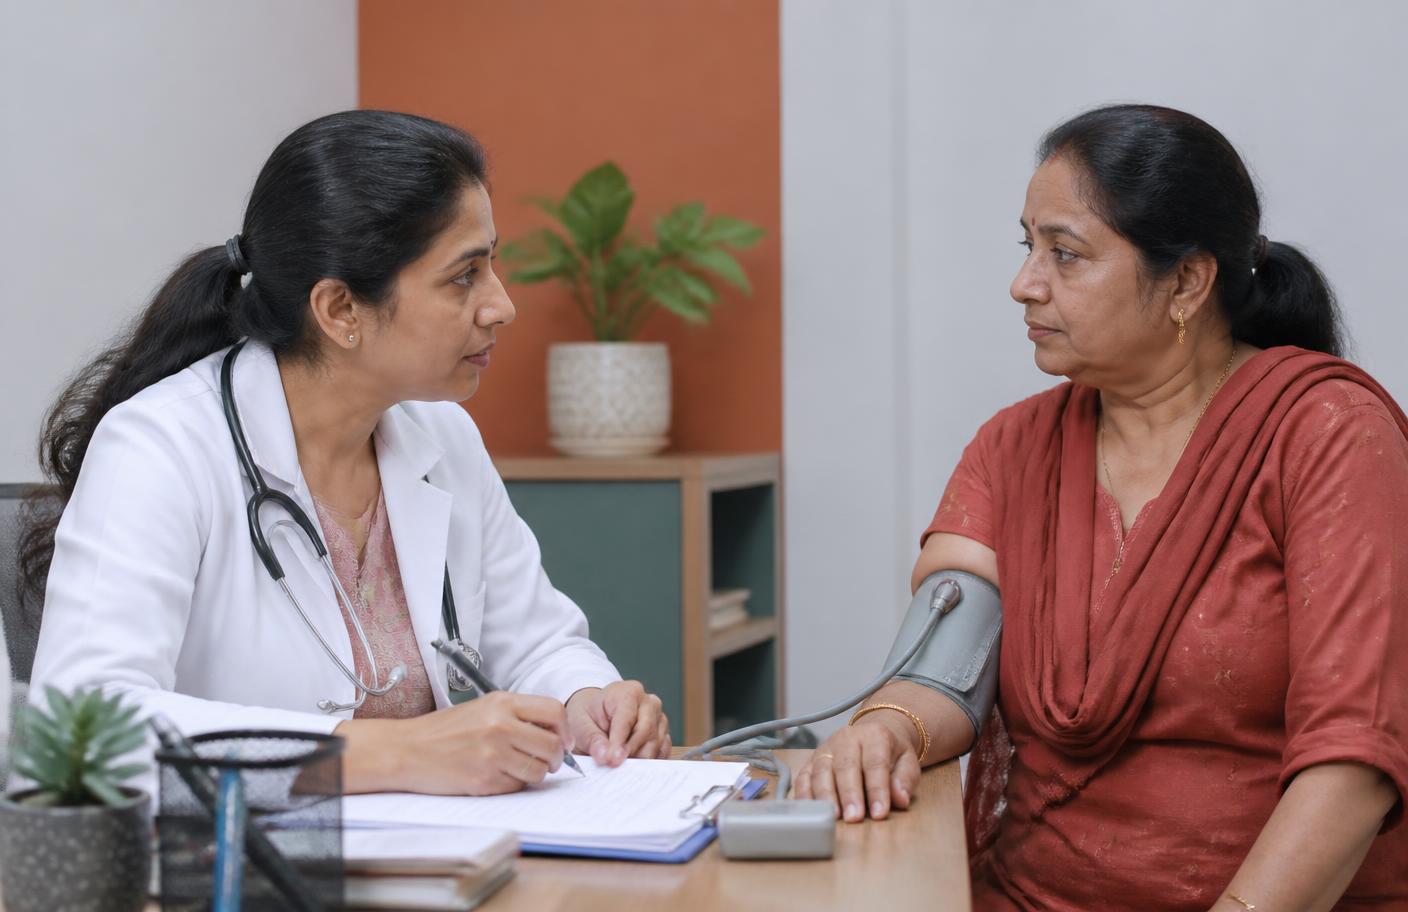Hot flushes may be the symptom everyone talks about, but menopause can also arrive as broken sleep, unexpected anxiety, vaginal dryness, or a feeling that your body no longer follows familiar rules. If you have searched for “Body-identical HRT menopause”, you may be wondering whether hormone treatment could help—and whether it is safe.
In my practice, I explain that menopause care is not a choice between “taking hormones” and “being natural”. It is about understanding your symptoms, assessing your health, and choosing support that fits your needs. Body-identical hormone replacement therapy (HRT) can be valuable for some women, but it works best within a personalised plan that includes nutrition, movement, sleep, and emotional wellbeing.
Understanding the transition to menopause
Perimenopause is the transition leading up to menopause. During this time, ovarian hormone production fluctuates, and periods may become shorter, longer, heavier, or less predictable. Menopause is usually confirmed after 12 consecutive months without a period, provided there is no other explanation and you are not using hormonal treatment that affects bleeding.
Symptoms can begin while periods are still regular. Alongside hot flushes and night sweats, you may notice:
- Difficulty falling asleep or waking repeatedly.
- Irritability, low mood, anxiety, or reduced concentration.
- Vaginal dryness, discomfort during sex, or urinary symptoms.
- Joint aches or changes in sexual desire.
These symptoms deserve attention, but they are not automatically caused by menopause. Thyroid problems, anaemia, medication effects, and other conditions can look similar. I assess the whole picture rather than attributing every concern to hormones.
For most women over 45 with typical symptoms, diagnosis is clinical; routine hormone testing is often unnecessary because levels fluctuate. Earlier symptoms, especially before 40, need a different assessment. HRT is not contraception, and pregnancy remains possible during perimenopause.
What body-identical HRT means
Body-identical HRT uses hormones with the same molecular structure as those produced by the human body. These commonly include estradiol, a form of oestrogen, and micronised progesterone, which is processed to help the body absorb it.
Oestrogen can be delivered through patches, gels, or tablets. If you still have your uterus, systemic oestrogen—treatment that acts throughout the body—usually needs to be paired with adequate progesterone or another suitable progestogen. This protects the womb lining from excessive thickening and reduces the associated risk of endometrial cancer.
After a total hysterectomy, oestrogen alone is often appropriate, although some medical histories require specialist advice. The regimen also depends on whether periods are continuing or have stopped.
I make an important distinction between regulated body-identical medicines and custom-compounded products marketed as “bioidentical”. Compounded preparations do not necessarily have the same evidence, quality control, or consistency as regulated medicines. Saliva tests used to tailor these mixtures are not a reliable basis for routine menopause prescribing.
“Body-identical” does not mean risk-free, and “natural” does not automatically mean safer. The formulation, route, dose, and your medical history all matter.
Balancing benefits with individual risks
Systemic HRT is an effective treatment for troublesome hot flushes and night sweats. It can improve sleep when symptoms are disrupting it and helps prevent bone loss while being taken. However, it is not a weight-loss treatment, a cure for every mood problem, or something I prescribe simply to prevent ageing.
For many otherwise healthy women with bothersome symptoms who are under 60 or within 10 years of menopause, the benefit–risk balance can be favourable. This is a starting point for discussion, not a guarantee of suitability.
Before prescribing, I review bleeding patterns, blood pressure, relevant medical history, medications, and personal and family cancer history. Previous blood clots, stroke, heart disease, liver disease, unexplained vaginal bleeding, or hormone-sensitive cancer may change whether HRT is appropriate or require specialist input.
The route matters. Oestrogen through the skin generally has a lower blood-clot risk than oral oestrogen and may be preferable when particular risk factors are present. Breast cancer risk depends on the type of HRT, duration of use, and individual factors. Combined HRT can increase this risk with longer use. Some evidence suggests micronised progesterone may have a more favourable risk profile than certain other progestogens, but uncertainty remains.
For vaginal dryness, painful intercourse, or some urinary symptoms, low-dose vaginal oestrogen may be sufficient without systemic HRT. It has minimal absorption and usually does not require added progesterone. A history of breast cancer warrants an individual discussion, often involving the oncology team.
Building a safe, whole-person treatment plan
I begin by asking which symptoms are most disruptive and what you hope treatment will change. Where HRT is suitable, I choose an individualised regimen and review symptom relief, side effects, and bleeding, usually after about three months and periodically thereafter. There is no single stopping date for everyone; continuing treatment requires regular reassessment.
Spotting can occur after starting or changing HRT, but heavy, persistent, or unexpected bleeding needs assessment. Any bleeding after established menopause should be discussed promptly, rather than assumed to be hormonal.
My 360-degree approach supports medical treatment without presenting lifestyle measures as a substitute when treatment is needed:
- Nutrition: Include adequate protein, vegetables, fibre, and calcium-rich foods, with vitamin D advice based on individual needs.
- Movement: Combine walking or other aerobic activity with strength and balance exercises.
- Yoga and mind-body care: Use comfortable yoga, breathing practices, and mindfulness to support stress management and wellbeing.
- Sleep: Keep consistent sleep timings and notice whether caffeine, alcohol, or late meals worsen symptoms.
For women interested in naturopathy, I discuss proposed remedies openly. Herbal products can interact with medicines, and evidence for many “hormone-balancing” supplements is limited.
If HRT is unsuitable or unwanted, evidence-based non-hormonal medicines and menopause-focused cognitive behavioural therapy can help. Persistent depression, anxiety, or sexual pain also deserves its own assessment.
Key takeaways
Menopause care should help you feel informed, supported, and more comfortable—not pressured into one treatment. Regulated body-identical HRT can relieve troublesome symptoms, but its safety depends on your health history, the preparation used, and ongoing review. In my practice, I combine evidence-based prescribing with nutrition, movement, yoga, and emotional support, while investigating symptoms that need separate attention. The goal is a practical, personalised plan that improves quality of life and respects your preferences as your needs change.
To schedule your personalized consultation with Dr. Munawwer Sana at Apollo Fertility in Kondapur, Hyderabad, or to arrange an online telehealth video consultation, click here to book your appointment.
Want a personalised plan based on your reports?
Book an online consultation with Dr. Sana, or see her at Apollo Fertility, Kondapur (Mon, Tue, Wed, Thu & Sat, 1:00 PM – 6:00 PM). No referral required.
References & clinical guidelines
- Indian Council of Medical Research — National ART Guidelines and the ART (Regulation) Act, 2021
- ESHRE — European Society of Human Reproduction and Embryology, clinical practice guidelines
- NICE CG156 — Fertility problems: assessment and treatment
- Royal College of Obstetricians and Gynaecologists — patient information and guidelines